

The Hidden Risks of Root Canals: Persistent Infection, Biofilms, and Long-Term Health Effects
How Persistent Infection, Apical Periodontitis, and Bacterial Biofilms Can Remain After Root Canal Treatment
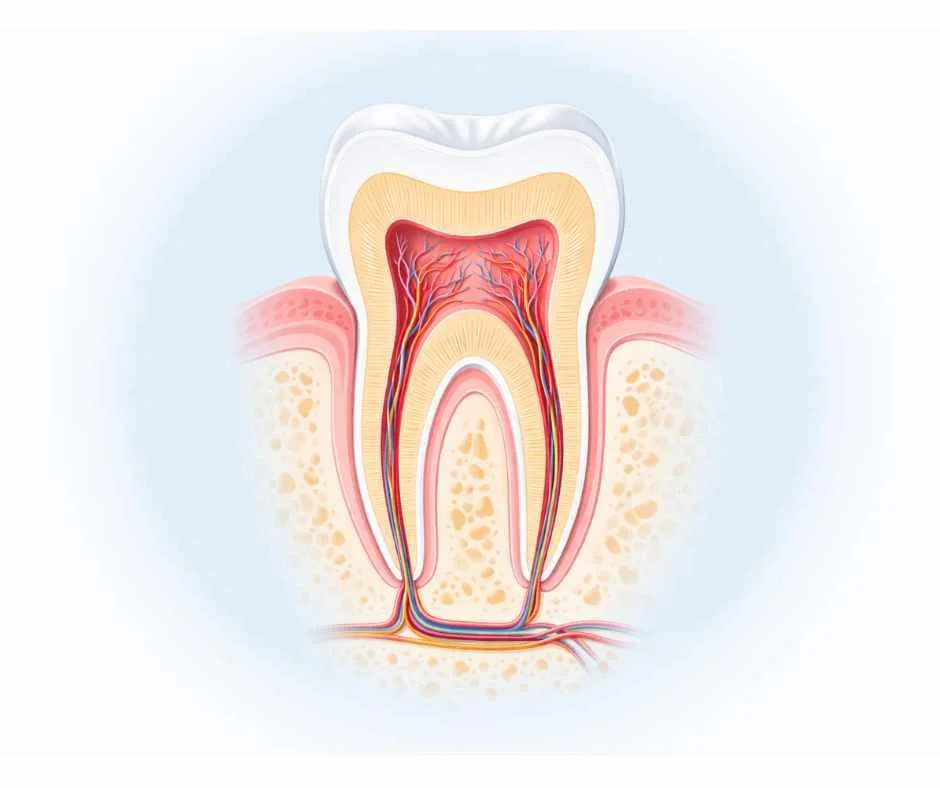
Root canal treatment is a standard procedure in conventional dentistry for preserving a damaged or infected tooth.
A root canal may stop the pain and retain the tooth, but it leaves behind a non-vital tooth. Because the area in and around the tooth cannot be completely cleaned and disinfected, bacteria remain and infection is likely to continue.
These bacteria and biofilms can remain for years without causing obvious pain or other dental symptoms, making ongoing infection easy to overlook.
When infection or inflammation remains around a root canal–treated tooth, the problem does not necessarily stay confined to the mouth. That ongoing source can continue to activate immune and inflammatory pathways long after the original tooth pain is gone. Chronic oral infections have been associated with cardiovascular disease, autoimmune conditions, and other chronic illnesses. They have also been studied in relation to certain cancers, particularly breast cancer, where persistent infection, immune activation, and chronic inflammation are biologically plausible contributors (1).
For patients already dealing with autoimmunity, chronic inflammation, fatigue, neurologic symptoms, or metabolic dysfunction, an unresolved dental infection can put fuel on the fire. A chronically infected or inflamed tooth adds another source of microbial exposure and immune activation to a system that may already be under significant inflammatory stress.
Saving the tooth and stopping the pain are not the only measures of a successful root canal. What matters long term is whether infection is truly controlled, the surrounding bone and tissue remain healthy, apical inflammation has resolved, and there is no ongoing microbial activity around the tooth.
Are Root Canals Safe? What Are the Long-Term Health Risks?
Root canals are not risk-free. They may stop the pain and keep the tooth, albeit dead, but bacteria can remain in areas that cannot be fully cleaned or disinfected.
The tooth may look and feel completely fine while infection, inflammation, and immune activation continueto smolder under the surface.
The long-term concerns are far-reaching. Persistent dental infection can add to systemic inflammation and immune dysregulation, while the treated tooth remains at risk for recurrent infection, apical periodontitis, structural weakening, and damage to surrounding bone or neighboring teeth.
What Is a Root Canal and Why Is It Controversial in Biological Dentistry?
A root canal is usually recommended when the pulp inside a tooth becomes infected from deep decay, a crack, or trauma. The infected tissue is removed, the canals are cleaned and disinfected, and the tooth is sealed so it can stay in place rather than being extracted.
From a conventional dental standpoint, that can look like a successful outcome: the pain is gone, the tooth is still there, and the infection has been treated.
That short-sighted outlook does not consider what may still be happening inside and around the tooth after the procedure—or how it can affect oral and systemic health down the line. Those are questions biological and holistic dentistry take much more seriously.
A root canal–treated tooth is no longer vital, and the internal anatomy is far more complex than the main canals that can be reached with instruments. Dentinal tubules, accessory canals, and microscopic irregularities can still harbor bacteria and biofilms after treatment (2).
The absence of pain does not necessarily mean the infection is gone. Bacteria, microbial byproducts, and inflammation can remain active around the root and in the surrounding bone, sometimes without obvious dental symptoms for years.
For someone already dealing with chronic inflammation, immune dysfunction, or other complex health issues, an unresolved dental source can become one more piece of the inflammatory load.
Why Can Infection Persist After a Root Canal?
A tooth is much more complicated inside than it looks on an X-ray. The main root canals are only part of the anatomy. Thousands of dentinal tubules branch through the dentin, along with accessory canals and other microscopic spaces that are difficult to reach during a root canal.
Bacteria are not always confined to the areas that can be cleaned with dental instruments and disinfecting solutions. They can penetrate deeper into dentinal tubules and form biofilms, making them much harder to eliminate. Once the pulp and blood supply have been removed, the tooth also loses the circulation and immune access that living tissue normally uses to respond to infection.
Anaerobic bacteria can continue to survive in this low-oxygen environment. They do not need to cause severe pain or another obvious abscess to remain active. Bacterial endotoxins and other microbial byproducts can continue to irritate the tissue around the root, while persistent infection can contribute to apical periodontitis and inflammation in the surrounding bone.
An old root canal can become relevant years later in someone with chronic health problems. The tooth may not hurt, and there may be no obvious outward sign of infection, yet chronic inflammation or infection can still be present around the root.
Resolving the original tooth pain is not the same as confirming that the infection is resolved. A root canal can remain functional for years while bacteria, apical inflammation, or changes in the surrounding bone continue beneath the surface.
What Are the Long-Term Risks of Root Canal–Treated Teeth?
The main concerns with root canal–treated teeth are persistent infection, chronic apical inflammation, bacterial endotoxins, structural weakening, and the systemic effects of an unresolved dental infection.
Persistent Bacteria and Biofilms After Root Canal Treatment
One of the central problems with root canal treatment is that the internal anatomy of a tooth cannot always be completely disinfected. Bacteria can remain in dentinal tubules, accessory canals, isthmuses, recesses, and other microscopic areas that are difficult to reach during treatment (1,2).
In a histobacteriologic study of teeth with apical periodontitis, intraradicular biofilms were found in approximately 80% of untreated teeth and 74% of previously treated teeth. Biofilms were also identified in anatomical areas such as ramifications and isthmuses that are difficult to reach with conventional cleaning and irrigation (2).
Concerns about bacterial persistence in root canal–treated teeth are not new. Weston A. Price investigated the relationship between infected teeth and systemic disease more than a century ago. Hal Huggins later reported DNA findings from root canal samples containing numerous anaerobic bacterial species, including Fusobacterium nucleatum, Porphyromonas gingivalis, Capnocytophaga ochracea, and Gemella morbillorum (3).
Modern endodontic microbiology now gives us a much clearer picture of what these earlier clinicians were observing. Persistent and secondary intraradicular infections are recognized causes of post-treatment apical periodontitis, and bacterial biofilms are well documented in previously treated root canal systems (1,2).
Chronic Inflammation and Immune Activation
When bacteria remain in or around a root canal–treated tooth, the immune response does not simply stop because the tooth no longer hurts.
Gram-negative bacterial endotoxins such as lipopolysaccharide can activate innate immune signaling and increase inflammatory cytokine activity in the tissues around the root. Persistent apical periodontitis involves interactions between microbial virulence factors and both innate and adaptive immune responses, with continued inflammation and progressive periapical bone loss in some cases (4).
For patients already carrying a higher inflammatory burden from autoimmune disease, metabolic dysfunction, chronic infection, environmental exposures, or other physiologic stressors, a persistent dental infection adds another source of immune activation. The mouth is part of the same inflammatory and immune system as the rest of the body.
Root Canal–Treated Teeth and Fracture Risk
Root canal–treated teeth are also more vulnerable structurally. Teeth that need root canals have often already lost substantial tooth structure from decay, cracks, trauma, or previous restorations. Accessing and preparing the canal can remove additional dentin and change how mechanical forces are distributed through the tooth.
Vertical root fracture is strongly associated with endodontically treated teeth, and current research points to several contributing factors, including dentin loss, preparation-related microcracks, reduced fracture resistance, restoration design, and occlusal forces (5).
A fracture can lead to additional procedures or eventual extraction, which makes structural integrity another long-term consideration when deciding whether to retain a severely damaged tooth.
Can Root Canal Infections Affect Systemic Health?
A chronic dental infection is not biologically confined to one tooth. The tissues around the root are vascular, lymphatically connected, and in constant communication with the immune system.
Persistent endodontic infection can contribute to bacteremia, inflammatory signaling, and low-grade systemic inflammation. Research has examined associations between apical periodontitis and cardiovascular disease, metabolic dysfunction, glycemic control, immune dysregulation, and other systemic conditions (4).
A systematic review and meta-analysis found that people with chronic endodontic infection had a 38% higher relative risk of cardiovascular disease compared with those without chronic endodontic infection (6).
Thomas Levy has also written extensively about infected root canal–treated teeth as reservoirs of bacteria and bacterial toxins that can reach tissues beyond the mouth through blood and lymphatic circulation. His work focuses heavily on the cumulative effects of chronic oral infection, oxidative stress, and systemic inflammatory burden (7).
Persistent oral infection deserves attention when chronic inflammatory or immune-related symptoms remain unexplained, especially when there is evidence of apical inflammation, recurrent infection, or a long-standing root canal–treated tooth.
→ Oral Health and Chronic Disease: How Gum Inflammation and the Oral Microbiome Impact Systemic Health
Is There a Link Between Root Canals and Breast Cancer?
The relationship between chronic dental infection, root canal–treated teeth, and breast cancer has been discussed for decades in biological dentistry and integrative medicine.
Thomas Levy has proposed that chronic oral infections can contribute to oxidative stress, inflammatory signaling, impaired immune function, and the tissue environment associated with malignancy (7).
Thomas Rau, former medical director of the Paracelsus Clinic in Switzerland, has been widely cited for reviewing 150 women with breast cancer and reporting that 147—approximately 98%—had one or more root canal–treated teeth located along the same meridian as the breast tumor (8).
Rau's findings came from a clinical review rather than a controlled epidemiologic trial, so the 98% figure should be understood as a clinical observation rather than proof that root canals cause breast cancer. The observation is still important because it points to a pattern that deserves further investigation.
Chronic infection, immune activation, microbial signaling, and changes in the tissue environment are all part of cancer biology (9). A chronically infected tooth adds another potential source of inflammation and ongoing immune stimulation.
For someone with breast cancer, a history of breast cancer, or significant chronic inflammatory illness, persistent oral infection should not be overlooked.
Root Canals and Dental Meridians
Traditional Chinese medicine has long described relationships between specific teeth, meridians, and organ systems. These relationships are also used by some biological dentists when evaluating dental pathology alongside symptoms elsewhere in the body.
Rau reported that the root canal–treated teeth he identified in women with breast cancer were located along the same meridians as the affected breast (8).
Meridian patterns can add another layer of information, especially when symptoms and dental findings repeatedly line up in ways that may not be obvious when a tooth is considered in isolation. Imaging, evidence of infection or inflammation, and the patient’s overall symptom pattern all add pieces to the holistic clinical picture.

How Root Canal Bacteria and Endotoxins Can Drive Systemic Inflammation
Persistent endodontic infections expose surrounding tissues to more than live bacteria. Bacterial cell-wall components, endotoxins, enzymes, and other microbial products can remain biologically active and continue driving inflammation (1,4).
Lipopolysaccharide from gram-negative bacteria is especially relevant because it activates Toll-like receptor signaling and downstream inflammatory pathways involved in cytokine production. These immune pathways contribute to persistent inflammation and bone resorption around infected roots and are also involved in systemic inflammatory signaling (4).
Huggins focused extensively on bacterial and toxic byproducts from root canal–treated teeth and their possible relationship to neurologic, immune, and systemic illness. His DNA testing work identified multiple anaerobic bacterial species in root canal samples, reinforcing his view that devitalized teeth can serve as reservoirs for biologically active microbes and their byproducts (3).
Peripheral inflammation can also affect the nervous system. Circulating inflammatory mediators can influence microglial activity and cytokine signaling in the brain, which is one reason chronic infection is considered in patients with brain fog, fatigue, headaches, cognitive changes, or other neurologic symptoms.
In a patient already dealing with autoimmune disease, chronic fatigue, neurologic symptoms, or persistent inflammation, an unresolved dental infection can add another source of microbial and immune stress.
→ Detoxification & Environmental Medicine
Root Canal Alternatives: Ozone Therapy, Extraction, and Biocompatible Implants
When a tooth has significant infection, recurrent apical inflammation, or poor structural integrity, a root canal is not the only option. Biological dentistry may also consider extraction, ozone therapy, and biocompatible tooth replacement, particularly when there is concern about leaving a non-vital or chronically infected tooth in place.
Tooth Extraction and Ozone Therapy
For a tooth with persistent infection or a poor long-term prognosis, extraction removes the diseased tooth rather than attempting to preserve it.
Ozone therapy is commonly used in biological dentistry after extraction because of its strong antimicrobial activity against bacteria, viruses, and fungi. Applied to the surgical site, ozone can help reduce microbial burden and support a cleaner environment for healing. Research has shown significant antimicrobial effects in dental applications, particularly when ozone is used alongside thorough debridement and proper surgical care (10,11).
Zirconia vs. Titanium Dental Implants
When an extracted tooth needs to be replaced, the implant material matters.
Titanium implants have a long history of use and predictable osseointegration, but titanium particles and ions can be released through corrosion, wear, and mechanical stress. Research has also documented inflammatory reactions around titanium implants in some patients (12,13).
Zirconia provides a metal-free alternative with excellent biocompatibility, resistance to corrosion, low plaque accumulation, and favorable soft-tissue response. It is often chosen by patients who want to avoid metal exposure or who have concerns about chronic inflammation or immune reactivity around titanium (14).
Bone quality, bite mechanics, periodontal health, implant location, and material tolerance all need to be considered when choosing the best replacement option.
How to Reduce the Risk of Needing a Root Canal
Many root canals begin with problems that have been developing for some time—deep decay, cracks, repeated dental work, periodontal disease, or untreated infection. Catching those problems earlier can reduce the chance that damage progresses into the pulp.
Prevention is not only about brushing and flossing. Oral microbiome balance, saliva production, mineral status, blood sugar regulation, diet, and the products used in daily oral care all influence cavity risk, gum health, and the ability of teeth and surrounding tissues to stay resilient.
Regular care with a biological or holistic dentist can also help identify problems before they become severe enough to require a root canal.
Fluoride Exposure and Oral Health
Fluoride is widely used for cavity prevention in conventional dentistry. Fluoride exposure is associated with dental and skeletal fluorosis, conditions in which teeth or bones can become abnormally mineralized—harder, yet more brittle and prone to cracking. Dental fluorosis can also cause white spots, mottling, or brown discoloration of the enamel. Higher fluoride exposure is also associated with thyroid dysfunction, altered thyroid hormone activity, neurodevelopmental effects, and fluoride accumulation in tissues such as bone and the pineal gland (15,16).
Hydroxyapatite-based toothpaste provides a safe remineralizing option without fluoride exposure or the risks associated with it.
PFAS in Dental Floss
Most conventional dental floss products use PFAS-containing coatings to make the floss smoother and more resistant to moisture. PFAS are persistent environmental chemicals associated with immune dysfunction, endocrine disruption, liver and kidney toxicity, and increased risk of certain cancers (17,18).
Using PFAS-free floss removes one avoidable source of daily chemical exposure.
Mouthwash, Nitric Oxide, and the Oral Microbiome
Strong antiseptic mouthwashes are designed to kill bacteria, but they do not distinguish between harmful and beneficial species.
The oral microbiome plays an important role in immune defense, digestion, protection against pathogenic organisms, and nitric oxide production. Frequent use of alcohol-based or broad-spectrum antiseptic mouthwash can disrupt this balance, contribute to dry mouth, and reduce nitrate-reducing bacteria that help produce nitric oxide (19).
Nitric oxide is critical for vascular function. It helps blood vessels relax, supports healthy blood flow, influences blood pressure regulation, and plays a role in endothelial function and tissue oxygen delivery. When oral nitrate-reducing bacteria are repeatedly suppressed, nitric oxide production can fall and vascular signaling can be impaired.
Research has linked frequent antiseptic mouthwash use with reduced nitric oxide availability, disruption of the oral microbiome, and higher blood pressure (19).
Non-Toxic Oral Care That Supports the Oral Microbiome
Oral health depends on more than what is used to brush and floss. A nutrient-dense diet, adequate protein, mineral sufficiency, healthy blood sugar regulation, and good saliva production all influence enamel strength, tissue repair, microbial balance, and resistance to decay.
High-quality nutrition should provide the minerals and fat-soluble nutrients needed for remineralization and periodontal health, including phosphorus, magnesium, food-based calcium, vitamin D, vitamin K2, vitamin C, zinc, and adequate protein.
Daily oral care should support that biology rather than repeatedly sterilizing the mouth. Useful options include:
Hydroxyapatite or other mineral-based toothpaste
PFAS-free dental floss
Natural-material instead of plastic toothbrushes
Herbal or microbiome-supportive oral rinses
Water flossing
Oil pulling
Regular mechanical plaque removal
The goal is to reduce pathogenic overgrowth, support remineralization, and preserve a healthy oral microbiome without adding unnecessary chemical exposure or disrupting beneficial bacteria (20).
Questions to Ask Your Dentist Before Getting a Root Canal
Before agreeing to a root canal, it is worth understanding how extensive the infection is, how much healthy tooth structure remains, and whether the tooth has a realistic long-term prognosis. A biological or holistic dentist can also provide a second perspective when there is recurrent infection, chronic illness, or concern about retaining a non-vital tooth.
Key Questions to Ask Before a Root Canal Procedure
What is the likelihood that the infection can be fully resolved with this procedure?
Understanding whether complete microbial eradication is realistic helps clarify the long-term outlook and whether ongoing monitoring will be needed.How extensive is the infection, and is there already inflammation or bone loss around the root?
Apical inflammation, bone changes, or infection extending beyond the main canal can affect prognosis and may change whether preserving the tooth is the best option.How much healthy tooth structure remains?
A tooth that has already lost significant dentin from decay, fractures, or previous restorations may have a higher risk of structural failure even after the infection is treated.Are there signs that infection extends into accessory canals, dentinal tubules, or surrounding bone?
Infection in areas that are difficult to reach mechanically may be harder to eliminate and can remain active even when the tooth is no longer painful.Are less invasive or biologically supportive options available?
Ozone therapy, laser-assisted disinfection, or other antimicrobial approaches may be considered as adjuncts or alternatives depending on the condition of the tooth and surrounding tissue.Would extraction provide a better long-term option for this tooth?
In a severely compromised or chronically infected tooth, removing the source of infection may be more appropriate than continuing to preserve a poor-prognosis tooth.If extraction becomes necessary, what replacement options are available?
Asking about zirconia implants, other biocompatible materials, timing, bone health, and long-term maintenance helps avoid making the replacement decision only after the tooth has already failed.
How Do You Decide Whether to Get a Root Canal?
The decision should involve more than whether the tooth can technically be saved. The extent of infection, condition of the surrounding bone, amount of healthy tooth structure remaining, history of recurrent dental problems, and any evidence of chronic inflammation all need to be considered.
For someone already dealing with autoimmune disease, chronic inflammation, fatigue, neurologic symptoms, environmental exposures, or other complex health problems, an unresolved dental infection deserves a closer look. In some cases, retaining the tooth may still make sense. In others, extraction and a biological approach to infection control and tooth replacement may offer a better long-term option.
At Denver Sports and Holistic Medicine, we do not perform dental procedures. We evaluate oral health as part of a holistic health picture, especially when chronic dental infection or inflammation may be contributing to persistent immune, gut, inflammatory, neurologic, or systemic symptoms.
When a dental evaluation is recommended, we collaborate with biological dentists who understand the relationship between oral infection and systemic health. Dental imaging and treatment decisions can then be considered alongside the patient’s medical history, inflammatory burden, environmental exposures, and other factors already being addressed in care.
Persistent dental infection should not be overlooked simply because the tooth is not painful. In a complex chronic illness case, identifying and addressing an unresolved oral source can be an important part of the evaluation.
Frequently Asked Questions About Root Canals
Are root canals safe long term?
Root canals can relieve pain and preserve a tooth, but long-term safety depends on whether infection is adequately controlled and whether the surrounding tissue and bone remain healthy. Bacteria can persist in dentinal tubules, accessory canals, and other microscopic areas that are difficult to disinfect completely. Recurrent infection, apical inflammation, structural weakening, and persistent microbial activity are the main long-term concerns.
Can a root canal stay infected without causing pain?
Yes. A root canal–treated tooth can have persistent infection or inflammation even when there is no pain. Chronic apical periodontitis, bacterial biofilms, and changes in the surrounding bone may remain relatively silent, which is why symptoms alone are not enough to determine whether a treated tooth is healthy.
Can root canals cause inflammation in the body?
Persistent infection around a root canal–treated tooth can continue to activate immune and inflammatory pathways. Bacterial endotoxins and other microbial products can stimulate local inflammation and may contribute to systemic inflammatory burden when the infection is chronic.
Can a root canal affect autoimmune disease or chronic illness?
A chronically infected or inflamed tooth can add another source of immune activation in someone already dealing with autoimmune disease, chronic inflammation, fatigue, neurologic symptoms, or other complex health problems. It does not mean the tooth is responsible for every symptom, but unresolved dental infection should not be overlooked in a comprehensive evaluation.
What are the signs of a failed or infected root canal?
Possible signs include pain with chewing, swelling, tenderness, gum drainage, recurrent abscesses, changes around the root on dental imaging, or bone loss near the tooth. Some infected root canal–treated teeth cause few or no obvious symptoms, so imaging and clinical evaluation may be necessary.
Is extraction better than a root canal?
Neither option is automatically appropriate for every tooth. The decision depends on the extent of infection, amount of healthy tooth structure remaining, condition of the surrounding bone, likelihood of completely controlling the infection, and the patient’s overall health. A severely compromised or chronically infected tooth may have a better long-term prognosis with extraction.
What is a biological alternative to a root canal?
Biological dentistry may consider extraction, ozone therapy, laser-assisted disinfection, and biocompatible tooth-replacement options depending on the condition of the tooth. If extraction is necessary, zirconia implants are one metal-free replacement option.
Can root canals be linked to breast cancer?
Clinical observations have reported associations between root canal–treated teeth, chronic dental infection, and breast cancer, but a direct causal relationship has not been established. Chronic inflammation, microbial activity, and altered immune signaling are biologically relevant to cancer development, which is why persistent oral infection deserves attention in patients with a history of breast cancer or significant chronic inflammatory illness.
How do I know whether an old root canal should be evaluated?
An old root canal deserves further evaluation when there is recurrent pain, swelling, bone loss, persistent apical inflammation, unexplained dental findings, or chronic inflammatory and immune-related symptoms that remain unresolved. A biological dentist can assess the tooth, surrounding bone, and imaging in more detail.
Still Have Questions?
If the topics above reflect ongoing symptoms or unanswered concerns, a brief conversation can help clarify whether a root-cause approach is appropriate.
Resources
International Endodontic Journal - Present Status and Future Directions: Microbiology of Endodontic Infections
Journal of Endodontics - Biofilms and Apical Periodontitis: Study of Prevalence and Association With Clinical and Histopathologic Findings
Huggins Applied Healing - Root Canals and Toxic Bacterium
Medicina - Association Between Endodontic Infection, Its Treatment and Systemic Health: A Narrative Review
Australian Endodontic Journal - Vertical Root Fracture in Endodontically Treated Teeth: Risk Factors and Future Directions
International Journal of Environmental Research and Public Health - Cardiovascular Disease and Chronic Endodontic Infection: Is There an Association? A Systematic Review and Meta-Analysis
Orthomolecular Medicine News Service - Root Canals Cause Breast Cancer—Frequently
The Julian Center for Comprehensive Dentistry - The Relationship Between Root Canals and Cancer
Nature Reviews Cancer - Context-Dependent Functions of Pattern Recognition Receptors in Cancer
Frontiers in Oral Health - The Use of Ozone in Oral Health Care: A Narrative Review of Current Evidence and Clinical Applications
Journal of Dentistry - The Application of Ozone in Dentistry: A Systematic Review of Literature
Acta Biomaterialia - Corrosion of Titanium Under Simulated Inflammation Conditions: Clinical Context and In Vitro Investigations
Journal of Prosthodontics - Titanium Corrosion Products From Dental Implants and Their Effect on Cells and Cytokine Release: A Review
International Journal of Oral & Maxillofacial Implants - Biological Complications and Peri-Implant Tissue Response of Zirconia Compared With Titanium Dental Implants: A Systematic Review and Meta-Analysis of Clinical Evidence
Environmental Research - Does Fluoride Exposure Affect Thyroid Function? A Systematic Review and Dose-Response Meta-Analysis
JAMA Pediatrics - Fluoride Exposure and Children's IQ Scores: A Systematic Review and Meta-Analysis
Environmental Research - Association Between Serum Levels of Perfluoroalkyl and Polyfluoroalkyl Substances and Dental Floss Use: The Double-Edged Sword of Dental Floss Use—A Cross-Sectional Study
Environmental Toxicology and Chemistry - Per- and Poly-Fluoroalkyl Substances and Human Health: A Review of Exposure Routes and Potential Toxicities Across the Lifespan
Journal of the American Dental Association - Influence of Mouth Rinse Use on the Enterosalivary Pathway and Blood Pressure Regulation: A Systematic Review
Journal of Dentistry - The Role of Hydroxyapatite-Based, Fluoride-Free Toothpastes on the Prevention and the Remineralization of Initial Caries Lesions: A Systematic Review and Meta-Analysis